Navigating the Post-Pandemic Landscape: Comprehensive Tracking of Medicaid and CHIP Enrollment and Unwinding Outcomes

The United States healthcare safety net has undergone one of the most profound structural and operational transformations in its modern history. Driven by shifting federal policy directives, legislative overhauls, and the monumental administrative undertaking known as the Medicaid "unwinding," millions of Americans have experienced changes to their health coverage. According to the latest monthly performance data released by the Centers for Medicare & Medicaid Services (CMS) and analyzed extensively by policy research organizations, the national healthcare landscape continues to adjust to these post-pandemic realities. As public health agencies, state administrators, and policy analysts parse the long-term trends extending through mid-2026, the data reveal critical insights into how millions of children, adults, and vulnerable populations interact with public insurance programs.

Historical Context and the Pandemic Baseline
To understand the current trajectory of Medicaid and the Children’s Health Insurance Program (CHIP), one must look back to the onset of the COVID-19 pandemic in early 2020. In March 2020, Congress enacted the Families First Coronavirus Response Act (FFCRA), which included a crucial continuous enrollment provision. This mandate prohibited states from disenrolling individuals from Medicaid during the public health emergency, ensuring uninterrupted healthcare access for tens of millions of Americans during an unprecedented global health and economic crisis.
As a direct result, national Medicaid and CHIP enrollment swelled to historic highs, serving as an essential economic and medical cushion. However, this period of continuous enrollment officially came to an end following legislative actions that decoupled the continuous coverage mandate from pandemic-era emergency declarations. This triggered the "unwinding period"—a massive, state-led administrative process to redetermine eligibility for every single person enrolled in Medicaid and CHIP.
The Unwinding Period: Renewal Outcomes and Disenrollments
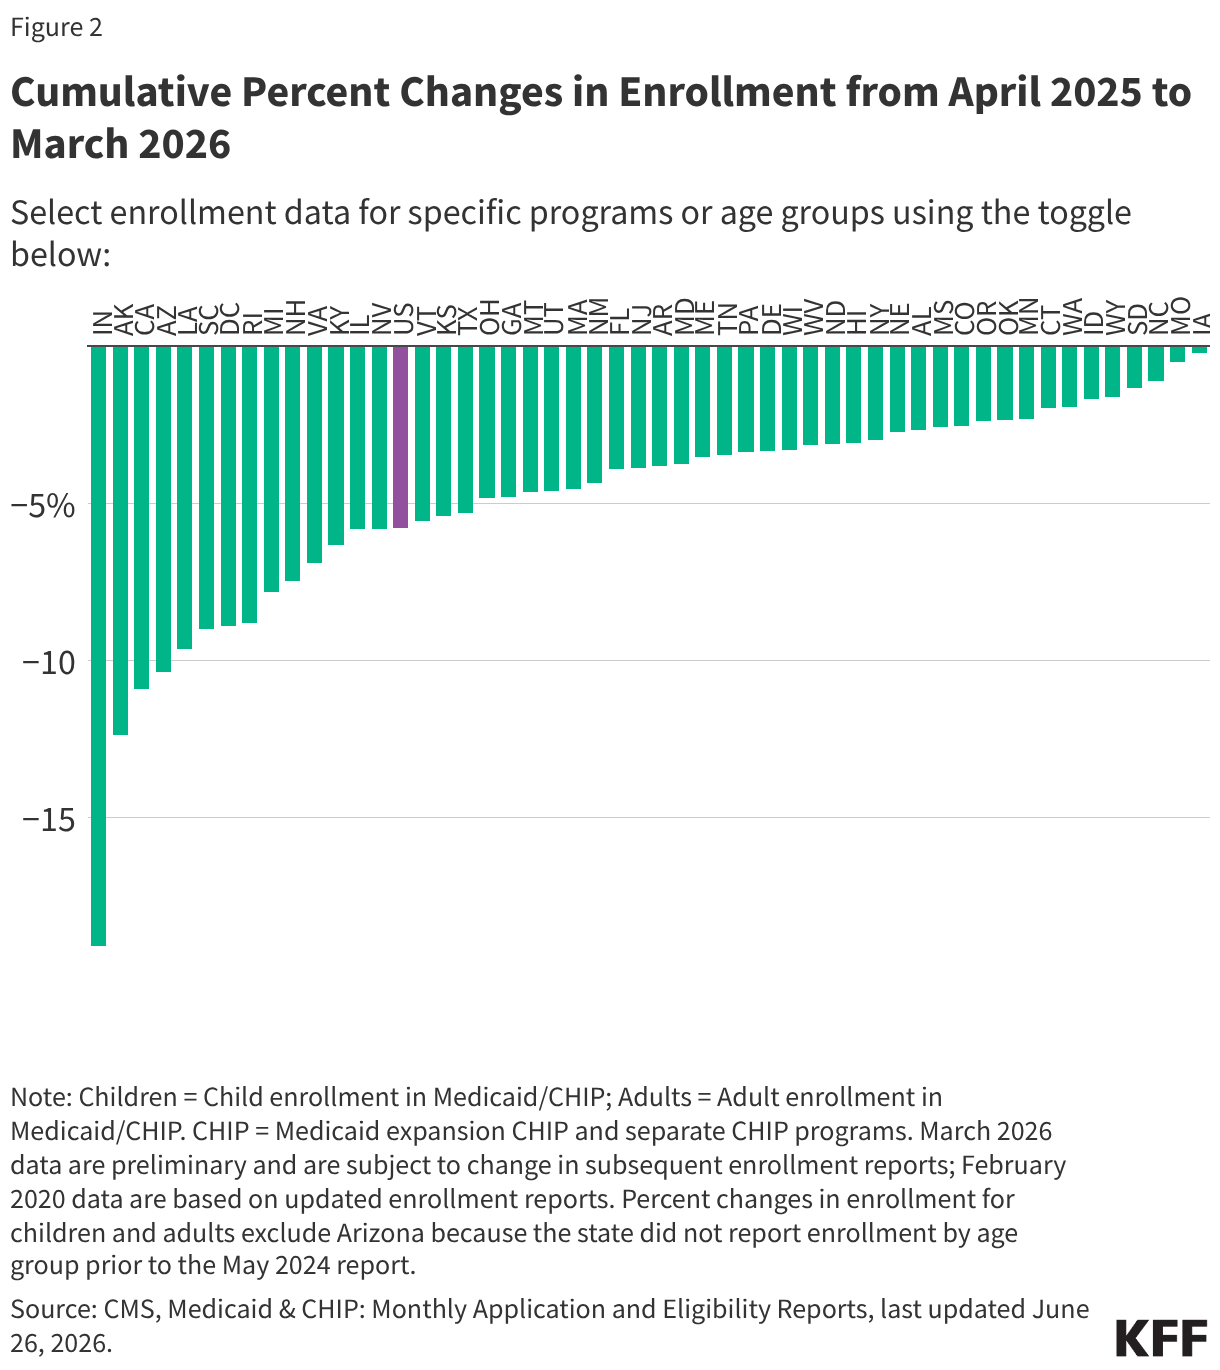
Beginning in early 2023 and largely concluding by late 2024, states embarked on the complex task of reviewing millions of cases. Archival and cumulative data finalized in late 2024 illustrate the staggering scale of this operation. As of September 12, 2024, states had successfully reported renewal outcomes for nearly nine out of ten individuals who were enrolled in Medicaid or CHIP prior to the start of the unwinding.
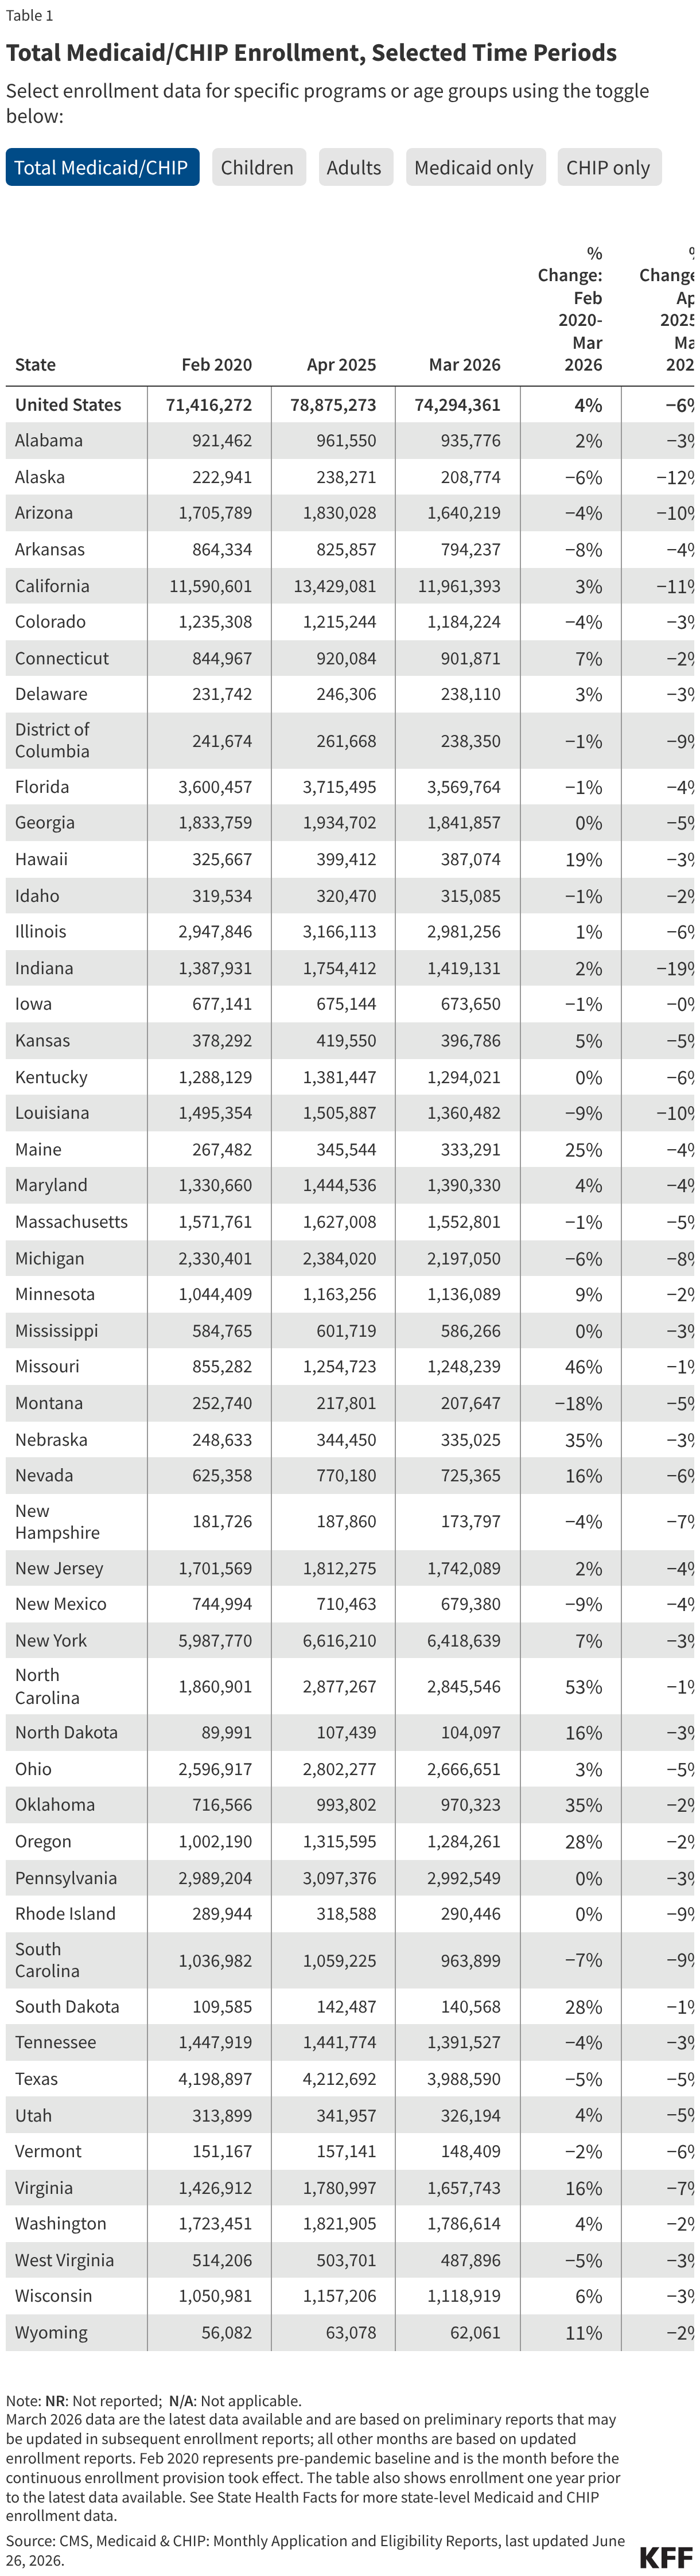
The cumulative metrics paint a stark picture of administrative churn and coverage loss. By the conclusion of the primary reporting window, at least 25,198,000 Medicaid enrollees had been disenrolled from the program, while roughly 56,378,000 individuals successfully had their coverage renewed. Disenrollment rates varied wildly across reporting jurisdictions, highlighting significant disparities in state-level administrative capacity and policy execution. For instance, disenrollment rates ranged from a high of 57 percent in Montana to a low of 12 percent in North Carolina among completed redeterminations.
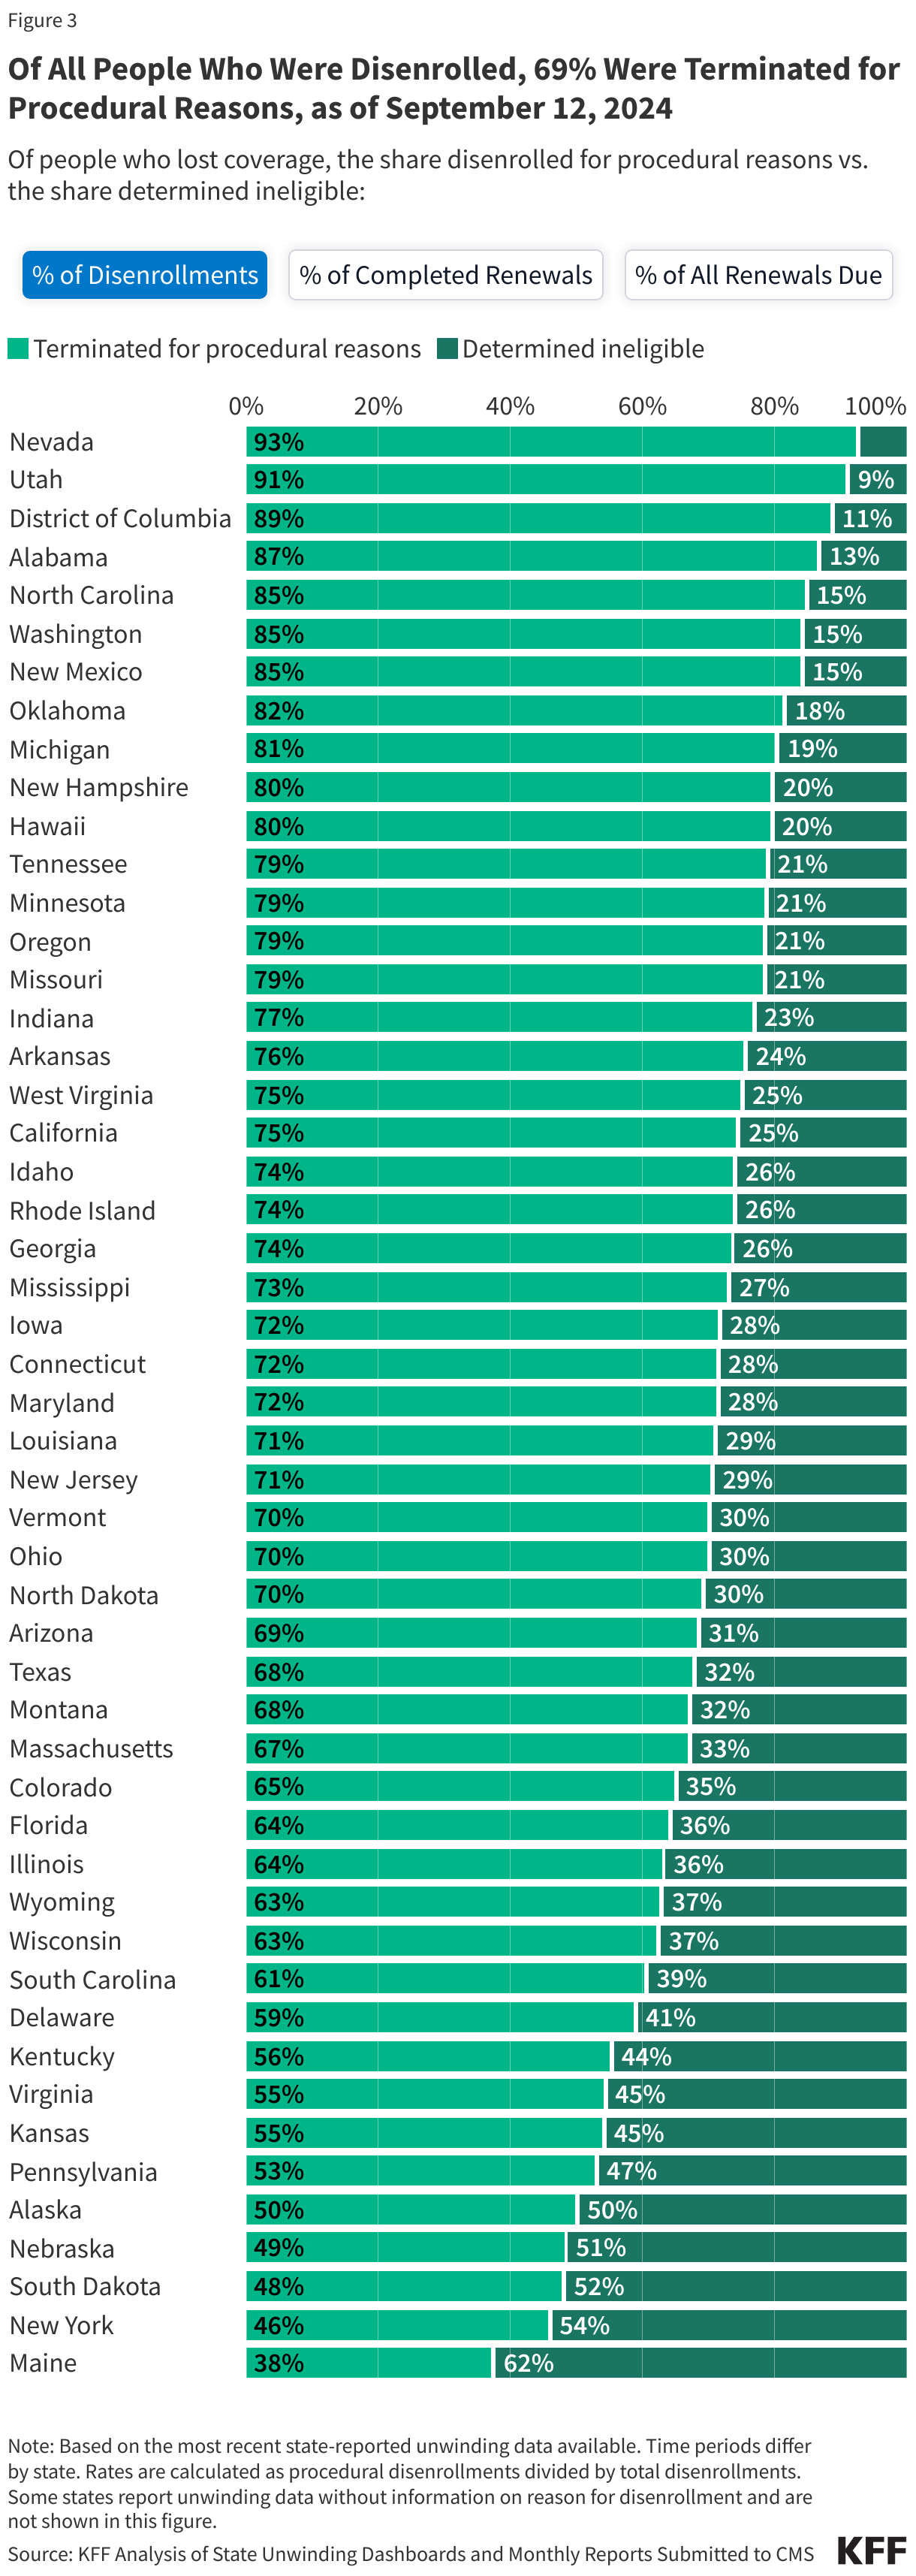
A particularly contentious aspect of the unwinding was the prevalence of procedural disenrollments—cases where individuals lost coverage not because they were formally determined ineligible based on their income or circumstances, but because they failed to complete the bureaucratic renewal paperwork. CMS and policy analysts noted that of all people who were disenrolled, an alarming 69 percent were terminated for procedural reasons. This translated to roughly 21 percent of all completed renewals resulting in procedural termination, underscoring systemic communication barriers, outdated contact information, and overwhelmed state processing systems.
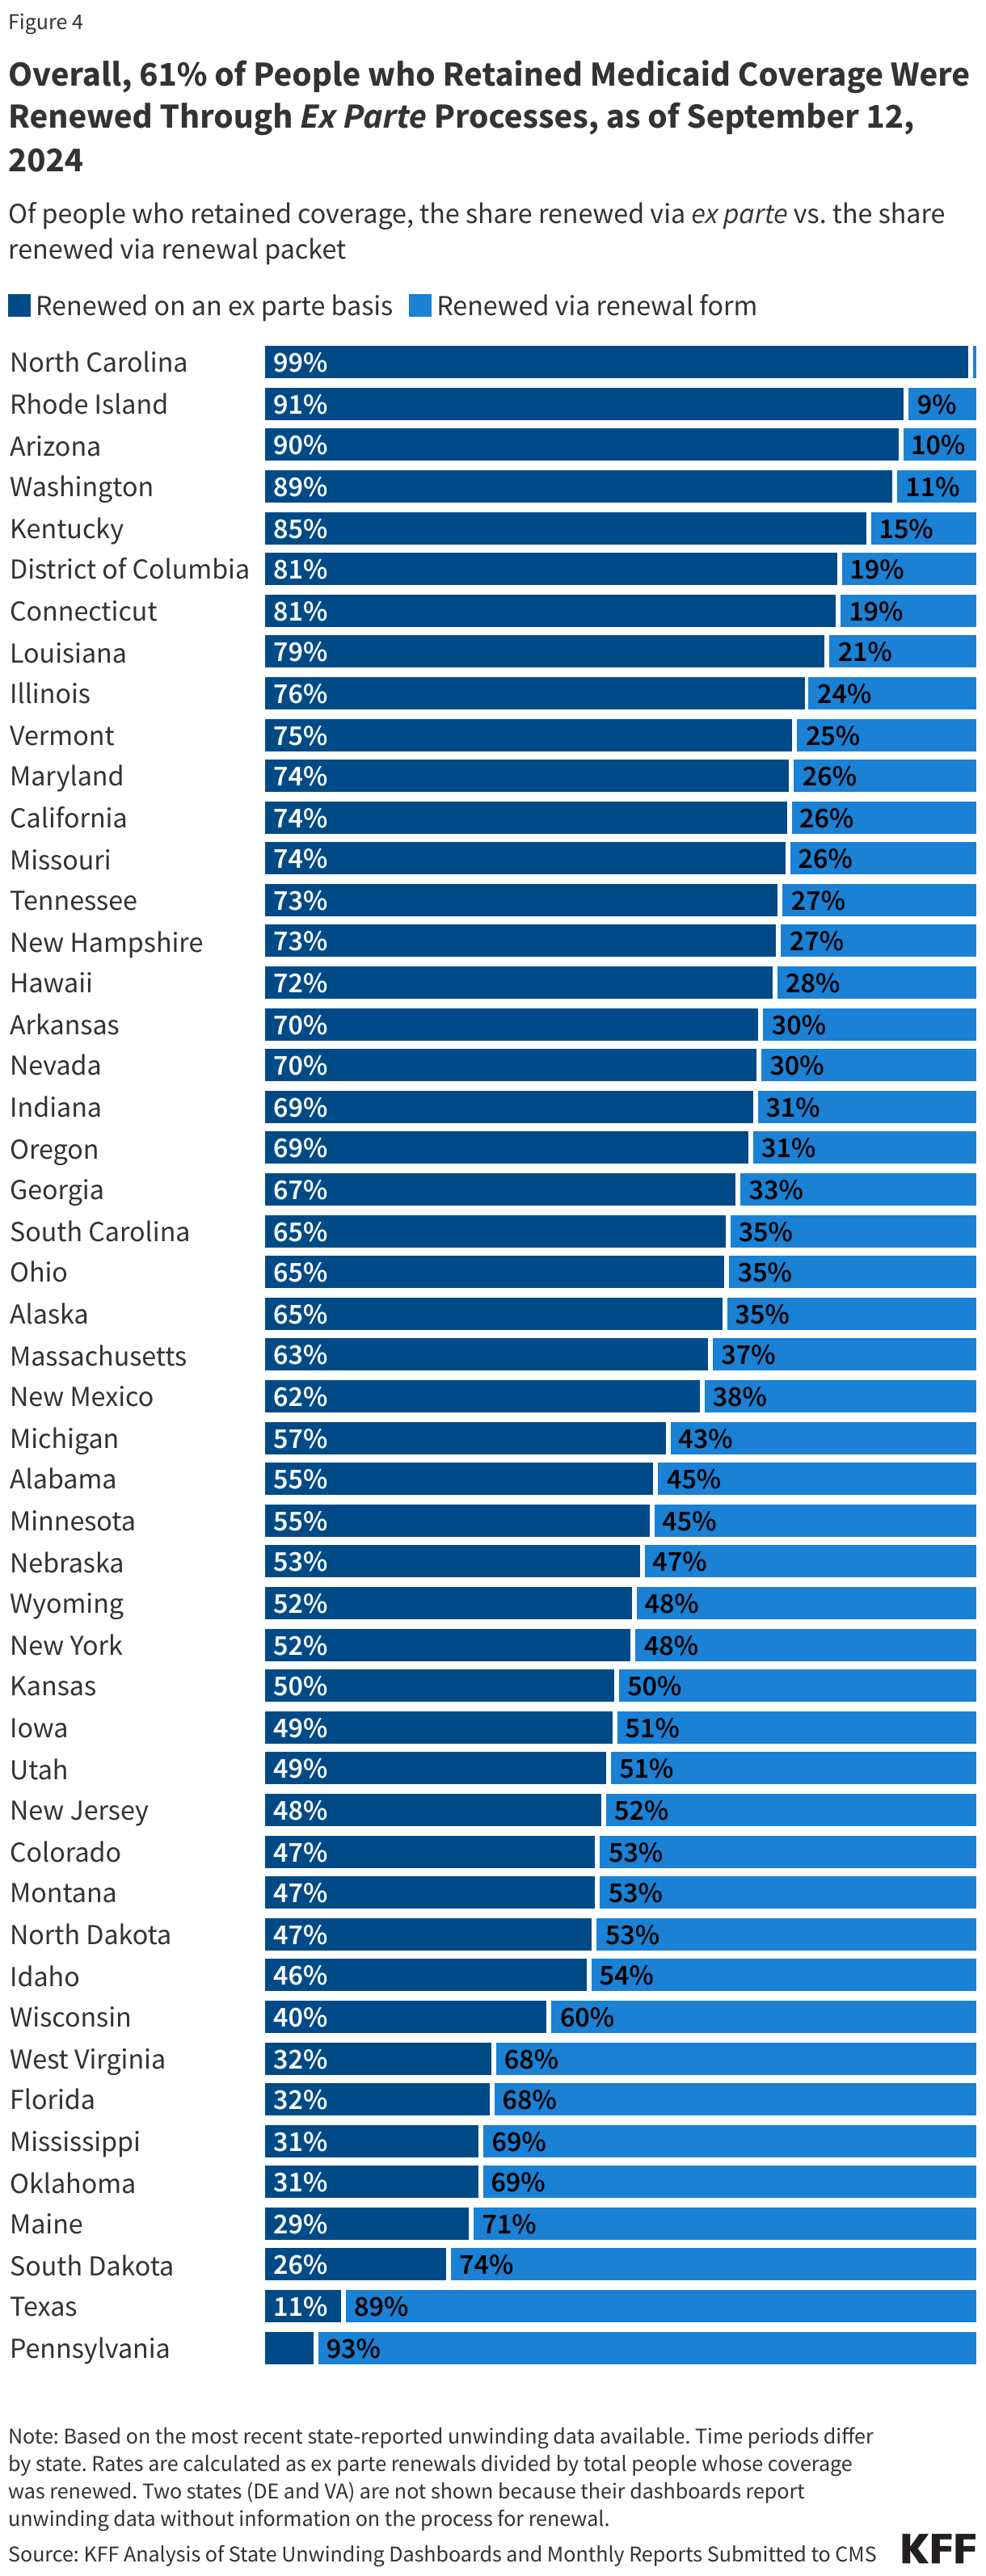
Conversely, for those who successfully retained their coverage, administrative efficiencies played a significant role. Overall, 61 percent of individuals who maintained their Medicaid coverage were renewed through automated "ex parte" processes, which utilize existing electronic data sources—such as wage databases—to verify eligibility without requiring direct action from the enrollee.
Current Enrollment Trends Through 2026
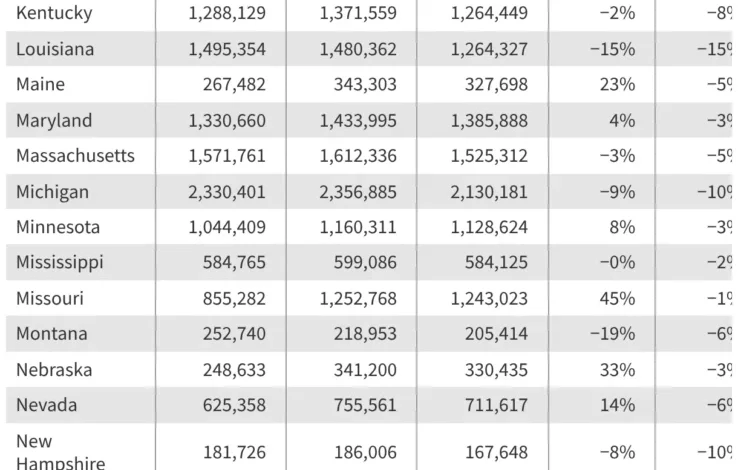
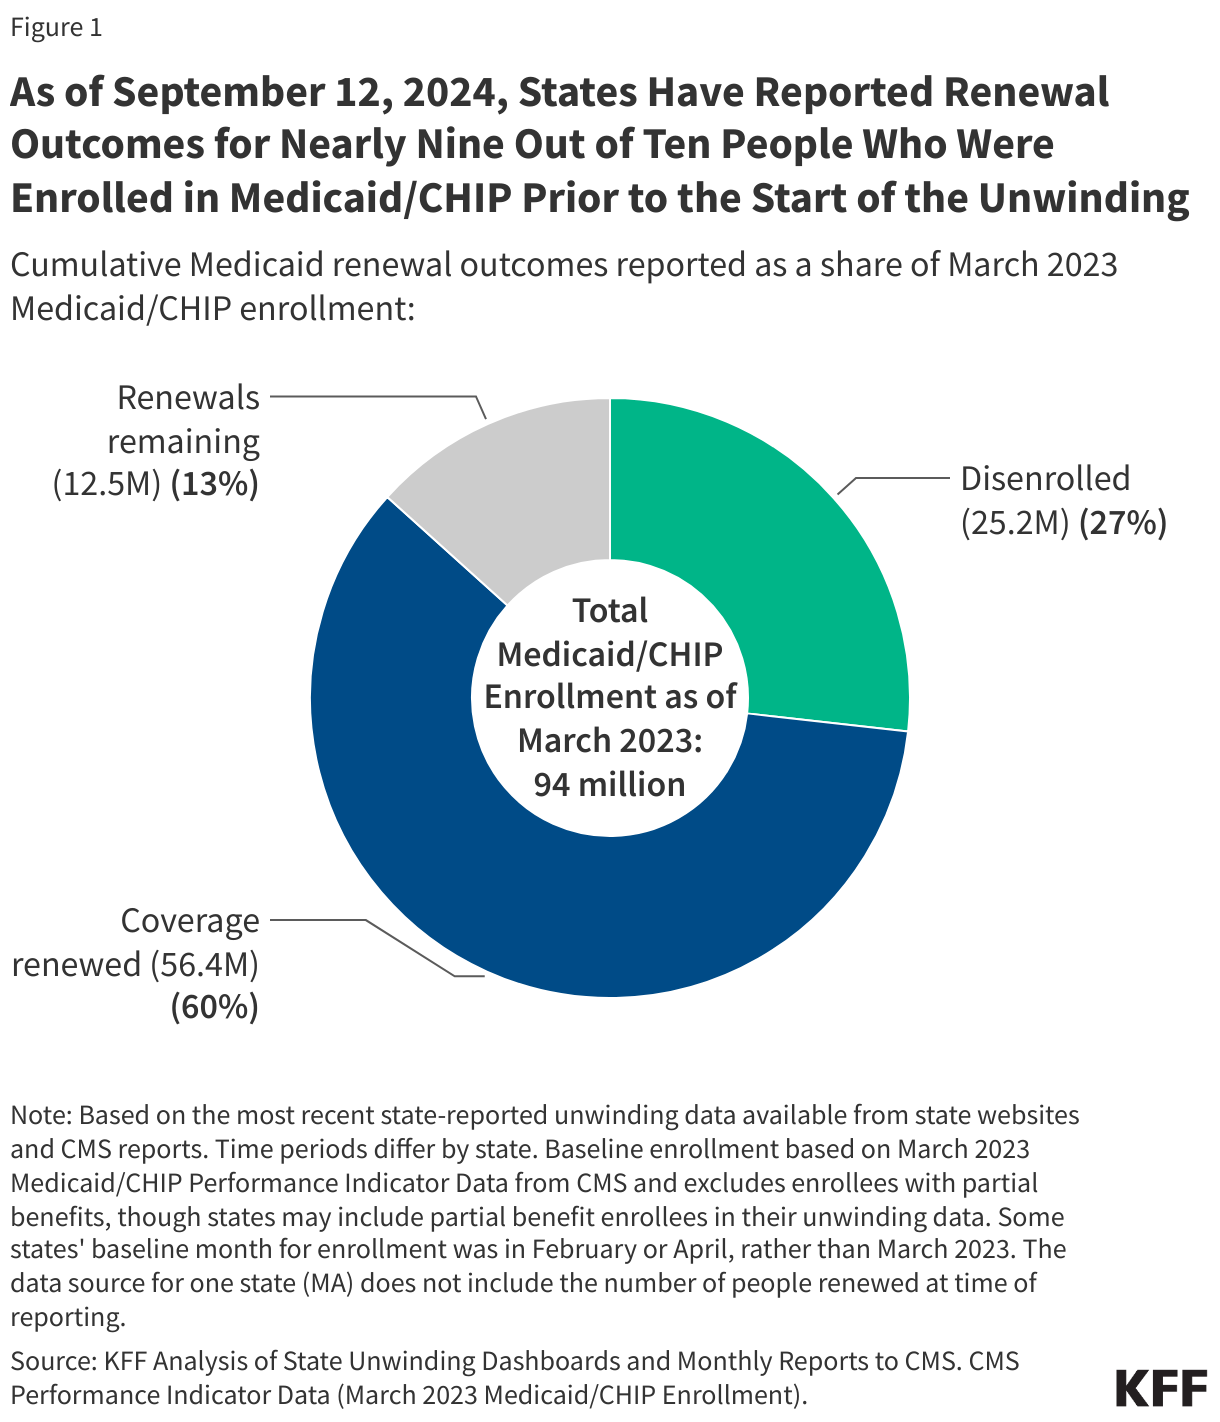
Fast-forwarding to current reporting periods ending in June 2026, the monthly data provided through the CMS Performance Indicator Project captures the post-unwinding stabilization and subsequent policy adjustments. While the data primarily capture full-benefit enrollees and exclude those with limited benefits (such as family planning-only coverage), they offer a reliable barometer for broader programmatic trends.
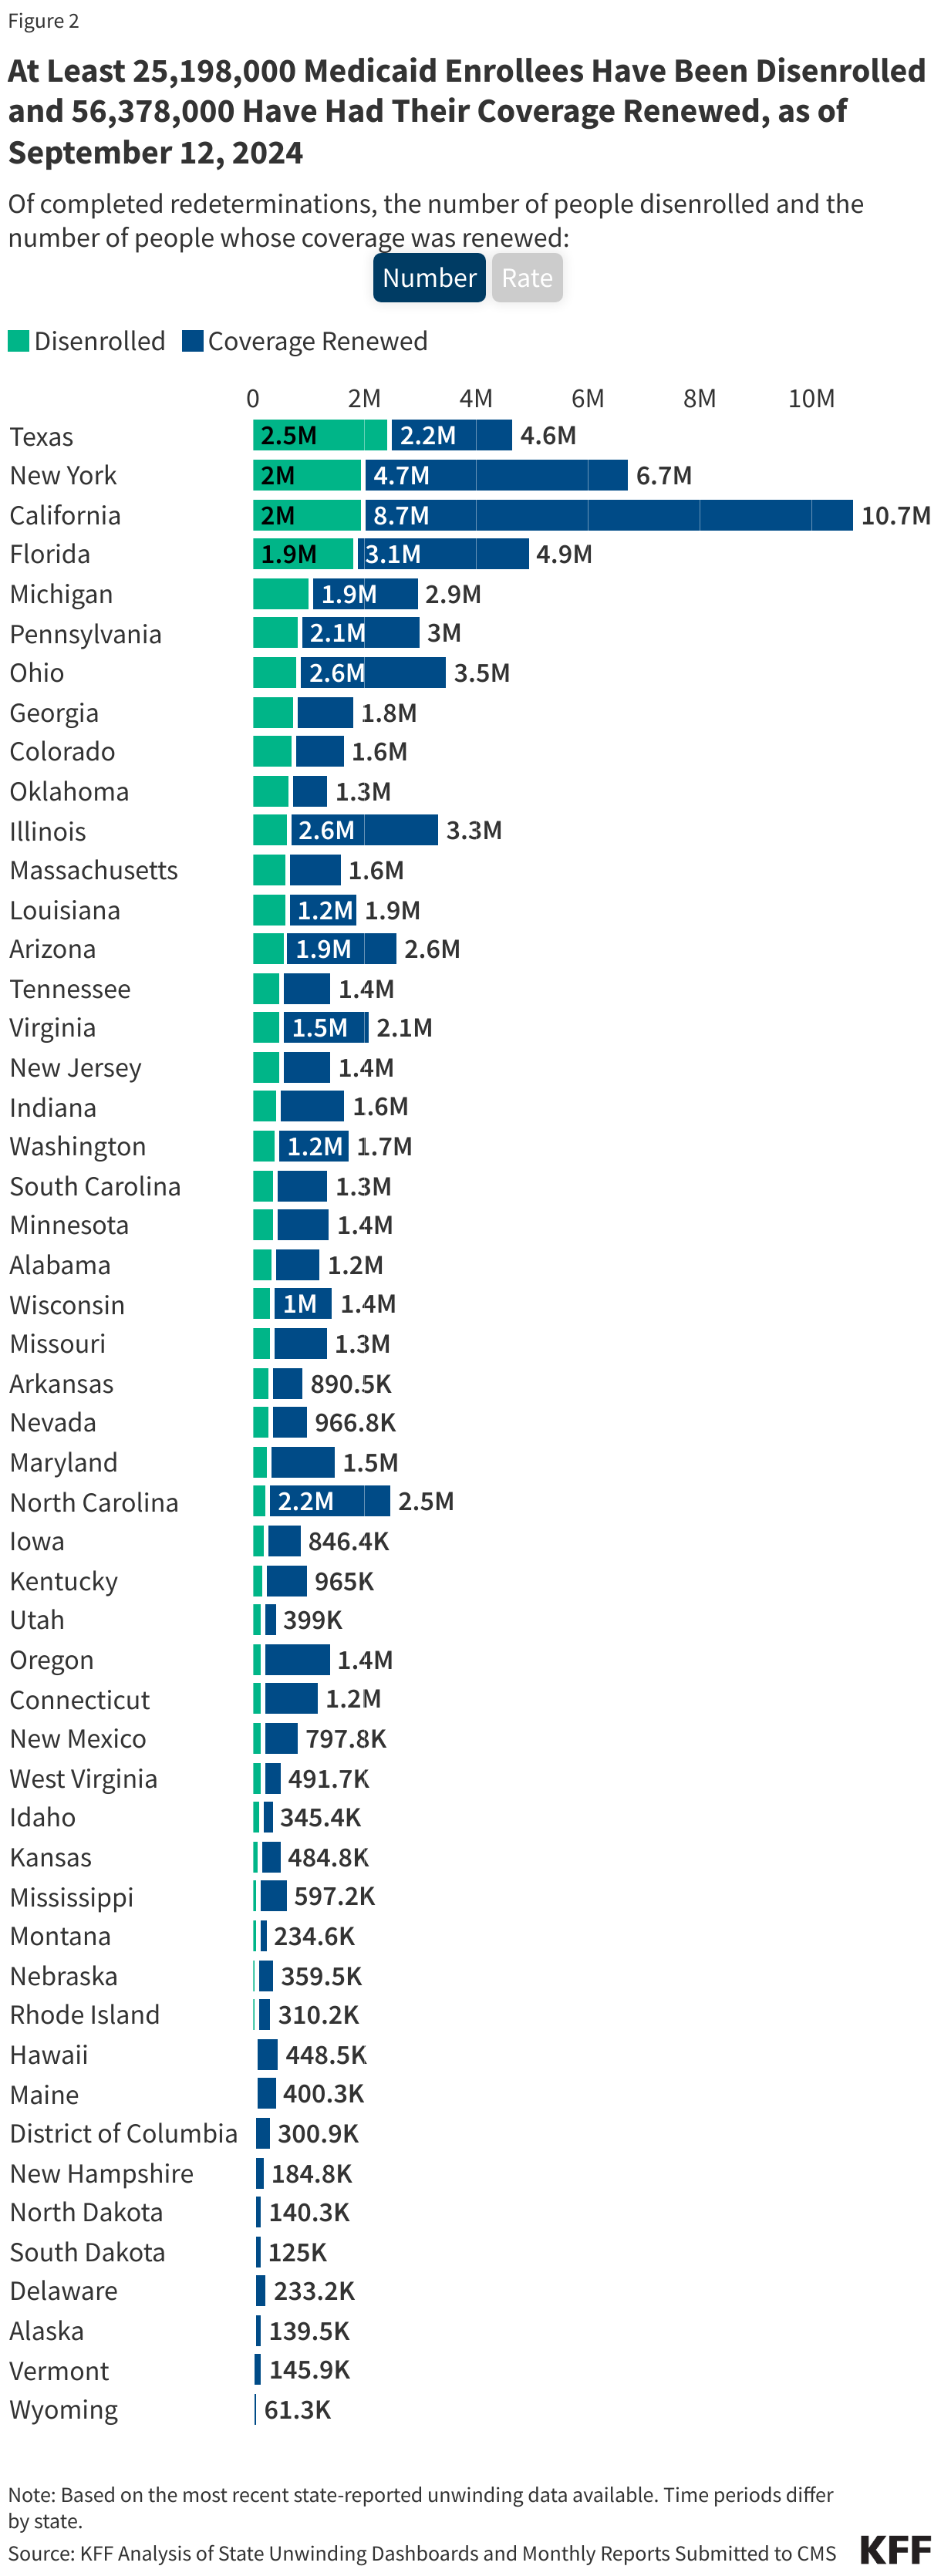
The figures through mid-2026 demonstrate how enrollment figures have settled following the massive contraction of the unwinding era. Child and adult enrollment metrics continue to be closely monitored by federal and state policymakers to detect any unmet healthcare needs or unexpected drops in coverage uptake. Analysts note that while preliminary monthly reports are subject to subsequent updates, the year-over-year comparisons between June 2025 and June 2026 provide a clear baseline of steady-state post-pandemic enrollment volumes.
Legislative Shifts: The 2025 Reconciliation Law and Future Projections
The regulatory environment governing Medicaid is poised for another seismic shift following the passage of the 2025 federal budget reconciliation law. This legislation introduced sweeping structural changes to the program, most notably requiring adults in the expansion group and certain Section 1115 waiver programs to satisfy stringent work and reporting requirements beginning in January 2027.
These new mandates are anticipated by budget experts and policy modelers to significantly reduce Medicaid enrollment over the subsequent decade compared to projections under prior law. Proponents of the work requirements argue they promote personal responsibility and employment engagement, while critics and healthcare advocates warn that administrative red tape will mirror the procedural disenrollment crises of the unwinding era, inadvertently stripping coverage from eligible, working-poor individuals who struggle to navigate reporting portals.
State health departments are currently deep into implementation planning, updating IT infrastructure, and drafting operational guidelines to comply with the 2027 deadlines. Organizations like KFF continue to track these developments closely, providing specialized monitoring tools and state-by-state analyses to measure how these upcoming mandates affect Medicaid expansion populations.
Implications for the Broader Healthcare Ecosystem
The convergence of historical pandemic-era expansions, the massive administrative churn of the unwinding, and upcoming work requirements carry profound implications for the American healthcare system.
For safety-net hospitals, community health centers, and primary care providers, fluctuations in Medicaid enrollment directly translate to shifts in uncompensated care costs and operating margins. When millions lose coverage—particularly through procedural disenrollments—patients often delay necessary care, leading to advanced disease progression and more costly emergency room interventions down the line. Conversely, successful ex parte renewals and robust outreach campaigns help preserve the continuum of care, protecting vulnerable populations from sudden financial shocks.
As the healthcare sector looks toward the full implementation of the 2025 reconciliation law’s mandates in 2027, transparency, timely data reporting, and cross-sector collaboration between state agencies and federal overseers will remain paramount. Ensuring that eligible Americans maintain access to essential healthcare services while modernizing administrative systems will define the next chapter of public health policy in the United States.