
New Federal Guidance Details Strict Medicaid Exemption Rules While Deepening Anxiety for Disability Advocates

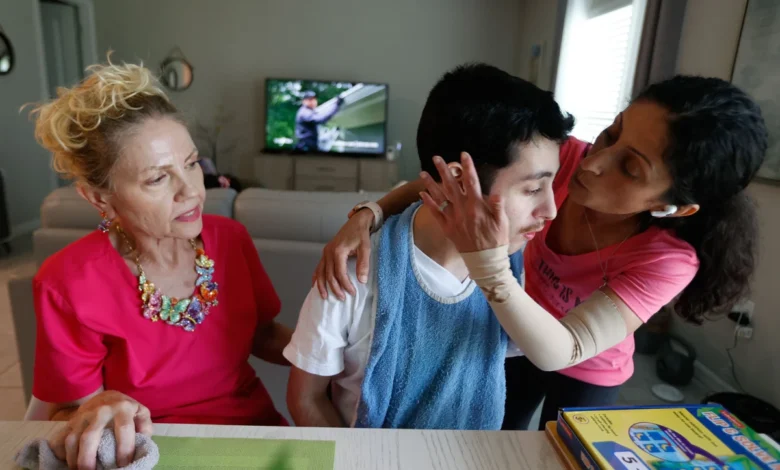
Federal health officials have released a comprehensive 33-page document detailing how states must operationalize complex exemptions to upcoming Medicaid work mandates. While the instructions aim to clarify administrative procedures for the Centers for Medicare and Medicaid Services (CMS), they have done little to alleviate widespread anxiety among healthcare professionals, state administrators, and advocacy organizations. At the core of the controversy is a narrow interpretation of "medical frailty," which critics argue diverges significantly from congressional intent and places vulnerable populations at unprecedented risk of losing vital healthcare coverage.
The release of this supplementary guidance represents the latest chapter in a turbulent policy shift that began with sweeping federal legislation. With most states mandated to enforce these new "community engagement" stipulations by the start of next year, the intersection of bureaucratic rulemaking and human welfare has ignited a fierce national debate over the future of public safety net programs in the United States.
Legislative Origins and the Push for Work Mandates
The architecture of the current policy crisis dates back to the legislative actions of 2025. Congress approved a massive budget reconciliation package—widely referenced as the One Big Beautiful Bill Act—which instituted nearly $1 trillion in cumulative cuts to the Medicaid program. Embedded within this legislation was a directive requiring states to establish community engagement criteria for non-elderly, non-disabled adult beneficiaries.
Under these statutory parameters, individuals enrolled in Medicaid must demonstrate active participation in qualifying activities for a minimum of 80 hours per month. Acceptable compliance metrics include traditional employment, vocational training, community service, or enrollment in an educational institution. Proponents of the legislation argued that such measures foster self-sufficiency and responsibly manage federal expenditures. However, lawmakers recognized that universal application of these rules would be catastrophic for individuals with severe medical conditions. Consequently, the statute explicitly exempted individuals classified as "medically frail" or those possessing "special medical needs"—a category encompassing physical, intellectual, and developmental disabilities. Furthermore, the legislative exemption extended outward to protect parents, legal guardians, and primary family caregivers who shoulder the responsibility of caring for individuals with significant functional impairments.
The Regulatory Shift and the Narrowing of Exemptions
Despite the broad protective language drafted by Congress, the administrative translation executed by CMS has drawn intense scrutiny. In June, federal regulators published baseline regulations that introduced stringent thresholds for claiming the medical frailty exemption. Rather than relying on a holistic assessment of a person’s condition, the CMS rule mandated that individuals with physical, intellectual, or developmental disabilities would only qualify as medically frail if their underlying condition demonstrably and significantly impaired their ability to perform at least one Activity of Daily Living (ADL).
The newly released 33-page guidance doubles down on this restrictive framework. It explicitly asserts that a condition qualifies an individual for an exemption only if the physical, mental, or behavioral health diagnosis directly and significantly obstructs their capacity to comply with the 80-hour monthly community engagement mandate. By tethering medical frailty strictly to work-readiness rather than clinical diagnosis, federal regulators have effectively reinterpreted the statutory language passed by Congress.
Legal experts and policy analysts have been quick to point out the administrative overreach inherent in this sub-regulatory approach. Nicole Jorwic, chief program officer at Caring Across Generations, articulated the frustration shared by many advocacy groups following the guidance publication.
"This updated guidance from CMS does attempt to provide more clarity, but doesn’t undo the overreach of the initial proposed final rule that is causing confusion for states, families, and people with disabilities," Jorwic stated. "Congress wrote a broad, clinically grounded definition of medical frailty into law specifically to protect people with serious conditions and disabilities. What we’re seeing now is the administration narrowing that definition through sub-regulatory guidance, without the transparency or accountability of formal rulemaking."
State Implementation Strategies and Administrative Burdens
The recent federal guidance outlines several methodological pathways for states to verify medical frailty and administer exemptions. To minimize administrative bottlenecks, CMS encourages state agencies to leverage existing data infrastructure. Under this model, states are directed to scan their internal databases and utilize the preceding 12 months of medical claims data to automatically identify individuals who meet the criteria.
In scenarios where automated data matching proves insufficient or inconclusive, states are permitted to accept a one-time self-declaration from the beneficiary. However, this preliminary relief is temporary; states are subsequently required to re-verify an individual’s exemption status on an annual basis "using reliable information or documentation."
To assist states with varying technological capabilities, CMS proposed an optional tiered evaluation framework:
- Tier One: States check an established list of clinical conditions that inherently qualify an individual for an exemption based on standardized diagnostic definitions.
- Tier Two: States evaluate a secondary list of conditions that strongly indicate medical frailty, pending the acquisition of supplementary confirmatory information.
- Tier Three: In cases where automated matching and tiered lists yield insufficient data, a manual administrative review is triggered.
While these procedural options offer a roadmap for state bureaucrats, policy specialists warn that the optional nature of the framework invites dangerous inconsistencies. Kim Musheno, senior director of Medicaid policy at The Arc of the United States, emphasized the inherent flaws of relying on historical claims data to evaluate lifelong disabilities.
"A claims record doesn’t always show how a disability affects someone’s daily life. That’s especially concerning for people with intellectual and developmental disabilities whose disabilities may be lifelong but aren’t reflected in recent medical claims," Musheno explained. "If the state’s data aren’t enough, the burden can shift back to the person to track down medical records or provider documentation."
Furthermore, Musheno expressed profound concern regarding the decentralized implementation model. Because the tiered framework is optional, states retain immense latitude to draft their own qualifying condition lists and verification protocols. This creates a fragmented regulatory landscape where a beneficiary’s access to an exemption could depend entirely on their geographic location. "Two people with the same disability could face very different processes and potentially different outcomes, simply because they live in different states," she noted.
Judicial Challenges and Interconnected Systemic Risks
The friction between federal regulators, state administrators, and advocacy organizations has rapidly escalated from policy debates into the courtroom. Earlier this year, a coalition consisting of officials from 25 states and the District of Columbia filed a major lawsuit challenging the legality of the CMS rules.
As that litigation progresses, the broader implications of the policy have galvanized the legal and advocacy community. This month, more than 70 organizations united to file an amicus brief supporting the state-led challenge. Signatories to the brief included prominent legal and civil rights organizations such as the National Health Law Program, the American Association of People with Disabilities, the Autistic Self Advocacy Network, and Easterseals.
Jane Perkins, litigation director at the National Health Law Program, underscored the psychological and administrative toll these rules impose on vulnerable populations. "Congress excluded medically frail people from the work requirements," Perkins said. "They should not have to repeatedly prove that they are unable to meet the work requirements."
The ramifications of narrowing the medical frailty exemption extend far beyond the loss of health insurance for individual beneficiaries. Industry leaders warn that the policy threatens to destabilize the entire ecosystem of community-based long-term services and supports. Barbara Merrill, CEO of the American Network of Community Options and Resources (ANCOR), highlighted the looming danger facing service providers.
"The new Medicaid work requirements will interrupt access to community-based services for people with disabilities and threaten the fragile network of community providers," Merrill cautioned. "The increased Medicaid coverage losses that will result from narrowing the medical frailty exemption will ultimately reduce access to services for people who truly need them and harm community providers who will continue to deliver support without receiving payment for their services."
Analytical Implications and Future Outlook
As the implementation deadline draws nearer, the collision between aggressive fiscal containment and the complex realities of disability support services creates a high-stakes environment for millions of Americans. By shifting the evidentiary burden onto individuals with intellectual, developmental, and physical disabilities—many of whom navigate daily life without robust technological or familial support systems—the policy risks driving eligible participants off the rolls due to procedural attrition rather than deliberate non-compliance.
The reliance on retroactive claims data, coupled with optional state-level verification tiers, virtually guarantees administrative variance and systemic friction. For community providers operating on razor-thin operating margins, an influx of administrative denials and subsequent coverage interruptions could trigger severe operational crises, imperiling residential facilities, vocational programs, and home health care agencies nationwide.
While CMS maintains that its guidance provides necessary structure for state execution, the silence from federal officials in response to ongoing criticism leaves many questions unanswered. As federal judges weigh the merits of the multi-state lawsuit and advocacy groups mobilize legal and legislative counter-measures, the true cost of these stringent Medicaid reforms will soon be tested against the stark realities of frontline health administration and human need.
Related posts:










