
New Federal Medicaid Guidance Deepens Anxiety for Individuals with Developmental Disabilities Amid Stricter Work Requirement Rules

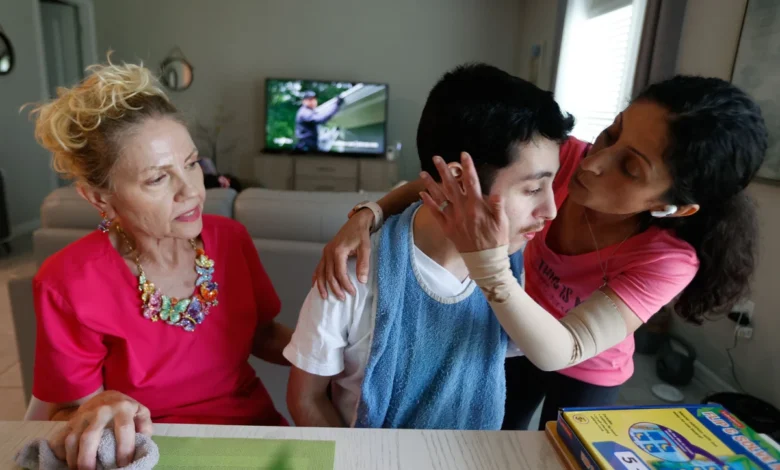
The Centers for Medicare and Medicaid Services (CMS) has released a comprehensive 33-page implementation document detailing how states must operationalize new, stringent Medicaid eligibility rules. Despite offering a framework for evaluating exemptions, the guidance has done little to alleviate widespread anxiety among advocates, families, and healthcare providers regarding how these modifications will affect vulnerable populations, particularly individuals with intellectual, physical, and developmental disabilities.
Under overarching federal legislation enacted last year, known as the One Big Beautiful Bill Act—which instituted nearly $1 trillion in sweeping Medicaid cuts—most states are mandated to implement “community engagement” requirements by the beginning of next year. These stipulations require non-exempt beneficiaries to verify that they are actively working, volunteering, or enrolled in school for a minimum of 80 hours per month to maintain their healthcare coverage. While the statute explicitly carves out exemptions for individuals classified as “medically frail” or those possessing “special medical needs,” recent regulatory actions have significantly narrowed the criteria required to secure these protections.
Background and Chronology of the Regulatory Shift
The legislative path leading to the current crisis began taking shape with the passage of the 2025 federal funding and policy overhaul, which introduced sweeping structural changes to safety-net programs. Aimed at curbing federal expenditures, the legislation granted states broad authority to tie Medicaid enrollment to work metrics, a concept historically debated across various political administrations.
However, recognizing the inherent barriers faced by severely ill or disabled individuals, Congress included explicit statutory language exempting anyone deemed medically frail, as well as their primary family caregivers, parents, and guardians.
The administrative implementation of these rules, however, has diverged sharply from what many congressional intent-makers and disability advocates originally anticipated. In June, CMS issued initial rules establishing that individuals with physical, intellectual, or developmental disabilities would only qualify for the medical frailty exemption if their conditions “significantly impair” their ability to perform at least one Activity of Daily Living (ADL). Such activities include fundamental life functions like bathing, dressing, walking, eating, toileting, or transferring in and out of a bed or chair.
The newly released guidance builds directly upon those June parameters, doubling down on the mandate that a qualifying health condition must directly impede a beneficiary’s capacity to fulfill the 80-hour monthly community engagement threshold. According to the document, “An individual in one of the five categories is considered medically frail only if the individual’s physical, mental, or other behavioral health condition significantly impairs the individual’s ability to comply with the community engagement requirement.”
Operational Framework and State Implementation Challenges
The guidance offers states multiple data-driven pathways to verify medical frailty, attempting to balance administrative efficiency with federal oversight. Foremost among these recommendations is the use of automated verification systems. CMS suggests that states analyze existing administrative records, leveraging the past 12 months of Medicaid claims data to automatically identify and exempt qualifying beneficiaries.
For cases where claims data proves inconclusive, states are permitted to implement a one-time self-declaration process for beneficiaries. Following initial approval, however, states must reverify a recipient’s medical frailty status every 12 months using “reliable information or documentation.”
To assist states in structuring their review processes, CMS proposed an optional tiered evaluation model:
- Tier One: States evaluate individuals against a definitive list of severe health conditions that automatically qualify for an exemption by their very definition.
- Tier Two: States review a secondary list of conditions that may indicate medical frailty, provided they are substantiated with supplementary clinical information.
- Tier Three: For complex cases lacking sufficient data from the first two tiers, a manual administrative review is triggered.
Despite these procedural frameworks, policy experts point out significant vulnerabilities in relying on historical medical claims. Kim Musheno, senior director of Medicaid policy at The Arc of the United States, noted that historical claims records frequently fail to capture the day-to-day realities of living with a lifelong disability.
“A claims record doesn’t always show how a disability affects someone’s daily life. That’s especially concerning for people with intellectual and developmental disabilities whose disabilities may be lifelong but aren’t reflected in recent medical claims,” Musheno stated. She further cautioned that when state data systems fall short, the administrative burden shifts back to individuals and families, forcing them to navigate complex medical systems to compile provider documentation and records.
Compounding these concerns is the fact that CMS designated its tiered review framework as optional rather than mandatory. This grants individual state governments wide latitude to design their own qualifying lists and assessment protocols, setting the stage for stark geographic disparities. Under this decentralized approach, two individuals with identical medical profiles could experience vastly different review processes and outcomes depending entirely on their state of residence.
Legal Challenges and Broad Opposition
The narrowing of the medical frailty exemption has catalyzed substantial pushback from legal organizations, state officials, and advocacy coalitions. Earlier this year, a coalition consisting of leaders from 25 states and the District of Columbia filed a major lawsuit in federal court challenging the legality of the CMS rules.
In a notable escalation of the legal battle, more than 70 national health, civil rights, and disability organizations filed a joint amicus brief supporting the state plaintiffs. Signatories to the brief included the National Health Law Program, the American Association of People with Disabilities, the Autistic Self Advocacy Network, and Easterseals, among others.
Jane Perkins, litigation director at the National Health Law Program, criticized the administration’s regulatory strategy, emphasizing that the sub-regulatory guidance exceeds executive authority and contradicts congressional intent.
“Congress excluded medically frail people from the work requirements,” Perkins said. “They should not have to repeatedly prove that they are unable to meet the work requirements.”
Critics argue that the administration is effectively rewriting statute through internal guidance documents rather than engaging in formal notice-and-comment rulemaking, thereby bypassing public transparency and accountability. Nicole Jorwic, chief program officer at Caring Across Generations, echoed these sentiments, noting that while the new guidance attempts to clarify state responsibilities, it fails to correct the fundamental overreach of the initial June rule.
“Congress wrote a broad, clinically grounded definition of medical frailty into law specifically to protect people with serious conditions and disabilities,” Jorwic said. “What we’re seeing now is the administration narrowing that definition through sub-regulatory guidance, without the transparency or accountability of formal rulemaking.”
Broader Implications for Healthcare Providers and Community Services
The potential fallout of the new Medicaid rules extends far beyond individual coverage terminations, posing a severe structural threat to the broader ecosystem of long-term services and supports (LTSS).
Barbara Merrill, CEO of the American Network of Community Options and Resources (ANCOR), warned that restricting the medical frailty exemption will generate a cascade of negative consequences for community-based providers who operate on notoriously thin financial margins.
“The new Medicaid work requirements will interrupt access to community-based services for people with disabilities and threaten the fragile network of community providers,” Merrill explained. “The increased Medicaid coverage losses that will result from narrowing the medical frailty exemption will ultimately reduce access to services for people who truly need them and harm community providers who will continue to deliver support without receiving payment for their services.”
As states race against the clock to establish verification systems ahead of the upcoming implementation deadline, thousands of disabled Americans and their families face mounting uncertainty. Without intervention from the federal courts or subsequent administrative revisions, advocates warn that administrative hurdles and narrowed exemptions will result in widespread coverage losses, leaving some of the nation’s most vulnerable citizens without the essential care and support structures they rely on to live safely in their communities. CMS did not respond to requests for comment regarding the ongoing litigation and implementation challenges.










