Navigating the 2026 Medicare Part D Overhaul: What Beneficiaries and Caregivers Need to Know

The landscape of senior healthcare finance is undergoing its most profound structural transformation in decades. Managing an older adult’s medication expenses has historically been a persistent financial drain, frequently characterized by convoluted coverage phases that made household budgeting nearly impossible for millions of families. However, the implementation of the Medicare Part D changes for 2026 has eliminated much of that volatility, introducing strict financial predictability to the prescription drug market through sweeping federal reforms enacted under the final phases of the Inflation Reduction Act.
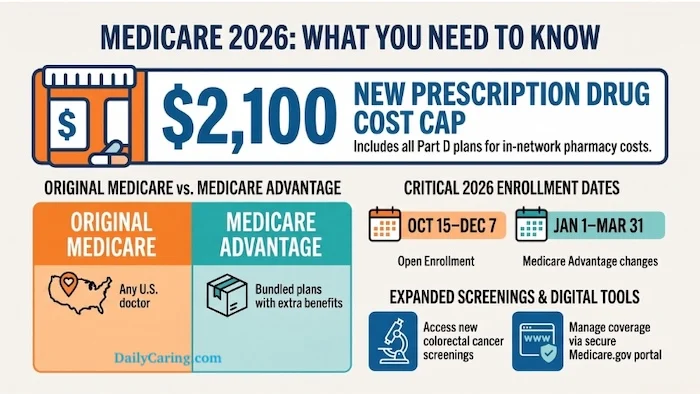
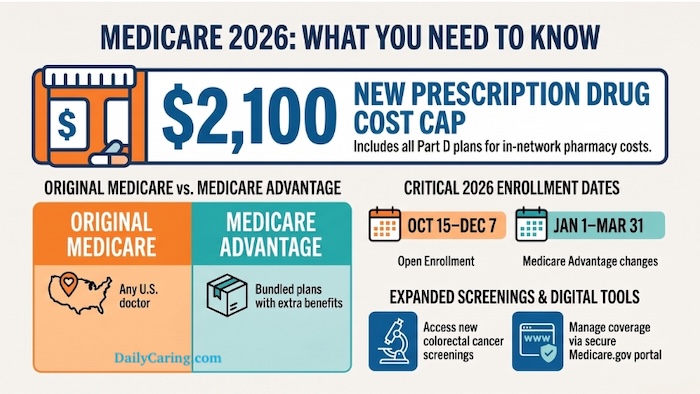
Under the updated regulatory framework, out-of-pocket costs for covered prescription drugs are now strictly capped at $2,100 annually for all beneficiaries. Furthermore, the maximum standard deductible for the 2026 plan year is legally set at $615. These sweeping alterations fundamentally reshape how seniors and their family caregivers plan for long-term eldercare expenses, offering a vital safety net against catastrophic pharmaceutical pricing. Yet, industry analysts and healthcare advocates caution that while direct consumer protections have never been stronger, insurance providers are shifting their strategies, making rigorous annual enrollment reviews more critical than ever.
The Permanent Demise of the "Donut Hole"
For well over a decade, the most notorious and financially destructive element of Medicare Part D was the coverage gap, universally known as the "donut hole." During this frustrating phase, seniors who reached a specific cumulative spending threshold suddenly became responsible for a massive percentage of their out-of-pocket drug costs until they finally qualified for catastrophic coverage. This abrupt financial cliff forced countless older adults to ration vital medications, skip doses, or make impossible compromises between paying for life-sustaining prescriptions and meeting basic household needs.

As of the 2026 plan year, the donut hole is permanently defunct. Under the modernized Medicare architecture, once an enrollee spends exactly $2,100 out-of-pocket on covered prescription medications in a single calendar year, their Part D plan or Medicare Advantage plan assumes 100% of the financial burden for the remainder of that year. There are no exceptions, and the archaic catastrophic coverage phase—which previously required patients to pay a 5% coinsurance fee even after meeting high thresholds—has been entirely eradicated. Once the $2,100 cap is reached, the patient’s cost for covered medications drops strictly to zero.
Chronology of Reform: From the Inflation Reduction Act to 2026
To fully understand the weight of the 2026 modifications, it is essential to examine the legislative timeline that brought about this regulatory evolution. The journey toward comprehensive prescription drug reform began in earnest with the passage of the Inflation Reduction Act (IRA) in August 2022. This landmark legislation established a multi-year phased rollout designed to gradually rein in soaring out-of-pocket pharmaceutical costs for Medicare beneficiaries.
- 2023: The implementation phase began with the freezing of insulin copaps at $35 per month for a one-month supply under Part D and Part B, alongside the elimination of cost-sharing for adult vaccines recommended by the Advisory Committee on Immunization Practices (ACIP).
- 2024: The catastrophic phase of Part D was modified, eliminating the 5% coinsurance requirement for beneficiaries who reached the catastrophic threshold, effectively making covered drugs free for the remainder of the calendar year once spending limits were met.
- 2025: The out-of-pocket spending cap for prescription drugs was introduced at a preliminary threshold of $2,000, while the standard deductible was adjusted to $545, setting the stage for full structural integration.
- 2026: The final implementation phase establishes the permanent $2,100 annual out-of-pocket cap (adjusted annually for inflation per statutory formulas) and the $615 standard deductible, while fully solidifying the elimination of the coverage gap and normalizing the broader availability of structured payment plans.
The Hidden Threat: Formulary Manipulation and Plan Shifts
Despite the robust financial protections guaranteed by the federal government, healthcare economists and consumer advocacy groups warn that beneficiaries must remain exceptionally vigilant during upcoming enrollment windows. Insurance companies and private plan sponsors are commercial enterprises that are not absorbing these mandated out-of-pocket caps out of corporate altruism. To compensate for the revenue constraints imposed by the federal government, carriers are aggressively restructuring their covered drug lists, commonly known as formularies.

In practice, this means insurance providers are increasingly shifting medications into higher pricing tiers, utilizing stricter prior authorization requirements, or dropping certain brand-name and specialty drugs from their formularies altogether. A medication that was fully covered and easily accessible in 2025 may face sudden exclusion or severe tier demotions in 2026.
Caregivers and seniors must meticulously verify that their specific, necessary medications remain explicitly listed on their chosen plan’s formulary during the Annual Enrollment Period. This step cannot be overstated: if a prescribed drug is not included on the plan’s official formulary, any money spent purchasing it out-of-pocket will not count toward the critical $2,100 annual cap, exposing the household to unmitigated financial risk.
Smoothing Costs: The Medicare Prescription Payment Plan
One of the logistical hurdles historically facing Medicare beneficiaries was the concentration of high medical and pharmaceutical expenses at the very beginning of the calendar year. When enrollees hit the pharmacy counter in January, they were frequently forced to pay hundreds of dollars upfront to clear their annual deductibles and initial coverage phase copays.
To mitigate this cash-flow shock, the federal government mandates the continuation and expansion of the Medicare Prescription Payment Plan for 2026. This voluntary, opt-in program is designed to smooth out-of-pocket prescription drug costs evenly across the entire calendar year.

Instead of paying a large, intimidating lump sum at the pharmacy counter, a beneficiary or their authorized caregiver can opt into the program. Under this arrangement, the pharmacy bills the insurance plan directly for the medication, and the insurance plan sends the enrollee a predictable monthly bill for their distributed share of the cost. Participation in this program does not reduce the overall amount spent on drugs, but it fundamentally transforms erratic, unpredictable medical expenses into manageable monthly budgeting increments.
Premium Stabilization and Market Realities
Another critical component of the 2026 regulatory framework is the federal premium stabilization program. When lawmakers debated capping out-of-pocket spending, regulators recognized a significant risk that insurance carriers might simply hike monthly base premiums to offset their projected liabilities under the $2,100 cap.
To counteract this potential loophole, the federal government instituted a statutory limit on base premium increases, capping annual hikes at 6%. However, financial analysts emphasize an important nuance: this stabilization cap applies specifically to the base premium calculation, not necessarily to every individual commercial plan’s final pricing structure. Consequently, individual plan premiums will continue to fluctuate based on regional market competition, carrier participation, and specific benefit packages.
This ongoing variability makes annual comparison shopping during the open enrollment window an absolute necessity for anyone seeking to minimize fixed overhead costs while maintaining robust medical coverage.
Broader Impact and Strategic Implications for Eldercare Planning
The integration of the 2026 Medicare Part D changes into broader eldercare financial planning represents a major paradigm shift for families managing aging loved ones. Historically, catastrophic medical bills were a primary driver of senior asset depletion, frequently forcing middle-class families to exhaust lifetime savings or rapidly spend down assets to qualify for Medicaid long-term care support. By establishing an absolute ceiling of $2,100 on annual prescription spending, federal policy has introduced a predictable framework that safeguards fixed-income households against financial ruin.
Nevertheless, financial planners stress that navigating these rules requires proactive engagement. Families are strongly encouraged to utilize official federal evaluation tools, consult independent State Health Insurance Assistance Programs (SHIP), or speak with qualified Medicare advisors before locking in their coverage selections.
As the healthcare market continues to adapt to these federal mandates, staying informed, reviewing annual plan notices of change, and verifying drug formularies remain the most effective tools for protecting both the health and financial security of America’s aging population.